
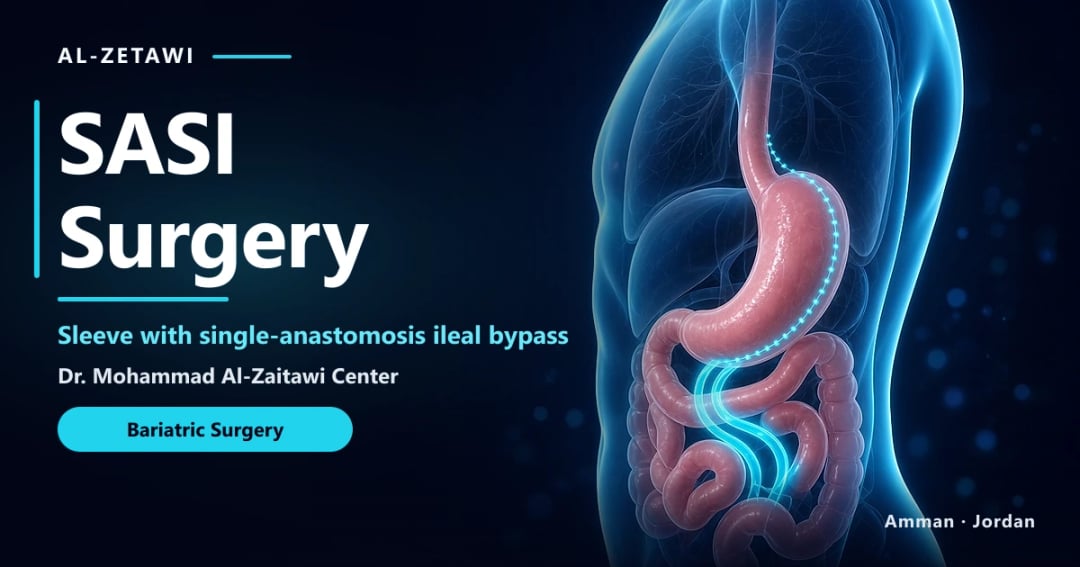
What Is SASI Surgery?
SASI stands for Single Anastomosis Sleeve Ileal bypass. It is a metabolic and weight loss operation that combines two steps in one procedure: a sleeve gastrectomy, which removes most of the stomach and leaves a narrow tube, and a single connection (anastomosis) between the lower part of that tube and the ileum, the last part of the small intestine. After SASI, food has two possible routes: the normal route through the pylorus and duodenum, and a shortcut route directly into the lower intestine.
The operation was described by the Egyptian surgeon Tarek Mahdy and colleagues, who published their first results in 2016. It builds on an earlier concept called sleeve gastrectomy with transit bipartition, introduced by the Brazilian surgeon Sergio Santoro, which uses a Roux-en-Y connection instead of a single loop. SASI simplifies transit bipartition by using one connection only, which shortens the operation and reduces the number of staple lines.
Why SASI was developed
Surgeons designed SASI to address some of the limitations of existing operations. Sleeve gastrectomy alone is effective but may lead to weight regain or reflux in some patients and has a more modest effect on long-standing diabetes. Gastric bypass is powerful but makes the duodenum and remnant stomach difficult to reach with an endoscope and bypasses the duodenum completely, increasing the risk of iron and calcium deficiencies. SASI aims to combine the restriction of a sleeve with the hormonal effect of early nutrient delivery to the ileum, while keeping the duodenum in the food pathway and accessible for endoscopy.
An important note on the evidence
SASI is a newer operation than sleeve gastrectomy or Roux-en-Y gastric bypass. Most published data come from observational studies, single-centre series and a small number of randomised trials, with limited follow-up beyond a few years. Early results are encouraging, but the long-term picture is still being established. Unlike sleeve gastrectomy, Roux-en-Y gastric bypass, one-anastomosis gastric bypass and single-anastomosis duodenal switch (SADI-S), SASI does not yet have formal endorsement from the American Society for Metabolic and Bariatric Surgery (ASMBS) as a standard primary procedure. Patients considering SASI should understand this and choose a centre that offers careful selection and long-term follow-up.
What this guide covers
This guide explains how SASI works, who may benefit, how it compares with other operations, what the current evidence shows, the risks and nutritional requirements, and what life after surgery involves. It draws on the original studies by Mahdy and colleagues, systematic reviews of SASI outcomes, the 2022 ASMBS and IFSO guidelines on indications for metabolic and bariatric surgery and the AACE/TOS/ASMBS nutrition guidelines, and is written by the team at Dr. Mohammad Al-Zaitawi's center in Amman.
How SASI Works: Bipartition Explained
The key concept in SASI is called bipartition, which means dividing the flow of food into two streams.
| Component | Typical description | Purpose |
|---|---|---|
| Sleeve gastrectomy | About 75 to 80 percent of the stomach removed, leaving a narrow tube, usually calibrated over a bougie | Restricts portion size and removes most of the ghrelin-producing stomach |
| Preserved pylorus and duodenum | The normal exit of the stomach remains open | Allows part of the food to follow the natural route, supporting absorption of iron, calcium and other nutrients |
| Gastro-ileal anastomosis | A side-to-side connection, commonly about 3 cm wide, between the lower stomach (antrum) and the ileum | Creates a shortcut that delivers part of each meal directly to the lower intestine |
| Distance from the end of the small intestine | The connection is commonly made about 250 to 300 cm before the ileocaecal valve | Aims to balance metabolic effect and nutritional safety |
The hormonal effect
When food reaches the ileum quickly, specialised cells release hormones, particularly GLP-1 and PYY. These hormones increase fullness, slow stomach emptying and stimulate insulin secretion after meals. This is the same mechanism thought to explain much of the metabolic benefit of gastric bypass and duodenal switch. In SASI, this effect is combined with the reduced hunger and restriction of the sleeve.
Why keeping the duodenum matters
Iron and calcium are mainly absorbed in the duodenum and upper small intestine. Because part of the food still passes through the duodenum after SASI, the procedure is intended to reduce the risk of iron deficiency, anaemia and bone problems compared with operations that bypass the duodenum entirely. Keeping the duodenum in continuity also means that the bile duct can still be reached with standard ERCP if gallstones block it later in life.
How the food actually divides
The proportion of food that takes each route varies between patients and may change over time. Some imaging studies suggest that, in a proportion of patients, most food eventually passes through the anastomosis rather than the pylorus. If this happens, the operation behaves more like a bypass, with a greater metabolic effect but also a higher risk of nutritional deficiencies. This is one reason why long-term nutritional monitoring is essential after SASI.
Who Is a Candidate for SASI?
The general indications for metabolic and bariatric surgery are set out in the 2022 ASMBS and IFSO guidelines: surgery is recommended for adults with a BMI of 35 kg/m² or more, and should be considered for those with a BMI of 30 to 34.9 kg/m² with metabolic disease such as type 2 diabetes, with lower thresholds for people of Asian ethnicity. Within these indications, SASI may be considered for selected patients.
Patients who may benefit from SASI
- Adults with obesity and type 2 diabetes, particularly when diabetes is poorly controlled despite medicines
- Patients with a high BMI and significant metabolic disease who want a stronger metabolic effect than a sleeve alone may offer
- Patients for whom endoscopic access to the duodenum and bile ducts is important, for example those with gallbladder or bile duct concerns
- Selected patients who prefer an operation that keeps the duodenum in the food pathway
- In some centres, patients with inadequate weight loss or weight regain after sleeve gastrectomy, when reflux is not the main problem
Patients for whom SASI is usually not recommended
- Patients with significant reflux disease, erosive oesophagitis or Barrett's oesophagus, because the sleeve component can worsen reflux; Roux-en-Y gastric bypass is usually preferred
- Patients with Crohn's disease or other chronic small-bowel disease
- Patients with chronic diarrhoea or malabsorption conditions
- People who cannot commit to lifelong supplements and laboratory monitoring
- Patients with untreated psychiatric illness, eating disorders or substance misuse until treated
- Active smokers, until they stop, because of the risk of ulcers at the connection
A decision for the multidisciplinary team
Because SASI is a newer operation with a developing evidence base, the decision should involve a detailed discussion of alternatives, including sleeve gastrectomy, Roux-en-Y gastric bypass and one-anastomosis gastric bypass. The surgeon should explain why SASI is being proposed for your specific situation and what the uncertainties are.
SASI vs Sleeve, Gastric Bypass, Mini Bypass and SADI-S
SASI is often compared with several other operations. Understanding the differences helps patients make an informed choice.
| Feature | Sleeve gastrectomy | Roux-en-Y gastric bypass | One-anastomosis (mini) bypass | SASI | SADI-S |
|---|---|---|---|---|---|
| Stomach | Sleeve; most of the stomach removed | Small pouch; rest bypassed but left in place | Long narrow pouch; rest bypassed | Sleeve; most of the stomach removed | Sleeve; most of the stomach removed |
| Intestinal change | None | Roux-en-Y bypass | Single loop bypass | Single loop connection to the ileum from the antrum | Duodenum divided and connected to the ileum |
| Pylorus and duodenum in food path | Yes | No | No | Yes, partly | Pylorus yes; most of the duodenum no |
| Endoscopic access to bile ducts | Normal | Difficult | Difficult | Preserved | Difficult |
| Reflux | May worsen | Usually improves | Bile reflux possible | Sleeve-related reflux and bile reflux possible | Sleeve-related reflux possible |
| Metabolic effect | Good | Strong | Strong | Strong in early studies | Very strong |
| Nutritional risk | Lower | Moderate | Moderate to higher | Moderate; depends on food routing | Higher; fat-soluble vitamins and protein |
| Society endorsement and evidence | Endorsed; large long-term evidence | Endorsed; large long-term evidence | Endorsed by IFSO and ASMBS; growing evidence | Not yet endorsed by ASMBS; limited long-term evidence | Endorsed by ASMBS; growing evidence |
SASI vs sleeve gastrectomy
SASI adds a bypass component to the sleeve. Early studies report greater weight loss and higher diabetes remission than sleeve alone, at the cost of a longer operation, an additional connection that can leak or ulcerate, and greater need for nutritional monitoring. For patients without diabetes or with a moderate BMI, a sleeve gastrectomy alone may be sufficient.
SASI vs Roux-en-Y gastric bypass
Roux-en-Y gastric bypass has decades of evidence and is the preferred operation for patients with reflux. SASI keeps the duodenum accessible and in the food path, but its long-term outcomes are less well established, and the sleeve component means reflux remains a concern.
SASI vs mini gastric bypass
One-anastomosis gastric bypass also uses a single connection but bypasses the duodenum entirely and leaves the remnant stomach in place. SASI removes most of the stomach and keeps the pylorus open. Both carry a risk of bile reflux into the stomach. Small randomised trials comparing the two report broadly similar short-term weight loss.
SASI vs SADI-S
SADI-S, the single-anastomosis duodeno-ileal bypass with sleeve gastrectomy, divides the duodenum just after the pylorus and connects it to the ileum, so all food bypasses most of the small intestine. It produces very strong weight loss and metabolic effects but a higher risk of protein and fat-soluble vitamin deficiencies. SASI is less malabsorptive because the normal pathway remains open, but it may also be less powerful in the long term.
Bipartition Variants: SASI, SASJ and Transit Bipartition
SASI belongs to a family of operations that share the same idea: a sleeve gastrectomy combined with a second outlet from the stomach to the small intestine, while the pylorus stays open. The main members of this family differ in how the second outlet is built and how much intestine is bypassed.
| Operation | How the second outlet is built | Main characteristics |
|---|---|---|
| Sleeve gastrectomy with transit bipartition (TB) | Roux-en-Y connection between the antrum and the ileum, with a separate connection further down | The original concept described by Santoro; avoids bile flowing into the stomach but requires two connections |
| SASI (single anastomosis sleeve ileal) | One loop connection between the antrum and the ileum, commonly about 250 to 300 cm from the ileocaecal valve | Simpler and faster than transit bipartition; bile reflux into the stomach is possible |
| SASJ (single anastomosis sleeve jejunal) | One loop connection between the antrum and the jejunum, closer to the start of the small intestine | Less intestine bypassed, intended to reduce the risk of malnutrition, with a possibly smaller metabolic effect |
Why the limb length matters
The total length of the small intestine varies considerably between people, from less than four metres to more than eight. A fixed measurement from the ileocaecal valve can therefore leave very different lengths of intestine in the bypassed segment and in the common channel. For this reason, many surgeons now measure the entire small intestine during surgery and adjust the position of the connection. A shorter common channel increases the metabolic effect but also the risk of diarrhoea, protein malnutrition and fat-soluble vitamin deficiencies.
Choosing between variants
There is no high-quality evidence showing that one bipartition variant is clearly better than the others. The choice depends on the surgeon's experience, the patient's BMI and diabetes severity, bowel function and the importance placed on minimising nutritional risk. What matters most is that the surgeon explains the design chosen, records the measurements in the operative note and provides long-term follow-up.
Patients who later need care elsewhere should keep a copy of their operative note, as other doctors will need these details to interpret symptoms, blood results and imaging correctly.
What the Current Evidence Shows
It is important to present the evidence on SASI honestly, including its limitations.
Early results
The first series published by Mahdy and colleagues in 2016 reported substantial excess weight loss and high rates of diabetes remission at one year in patients with obesity and type 2 diabetes. Since then, studies from Egypt, the Middle East, Europe and Asia have reported similar early outcomes. Systematic reviews and meta-analyses of these studies have reported pooled excess weight loss of roughly 70 to 90 percent at one year and high rates of improvement or remission of type 2 diabetes, hypertension and dyslipidaemia.
Limitations of the evidence
- Most studies are retrospective or single-centre, with relatively small numbers of patients
- Follow-up beyond two to three years is limited, and long-term data on weight regain and nutritional deficiencies are scarce
- Technical details vary between centres, including the sleeve size, the width of the connection and the distance from the ileocaecal valve
- Definitions of diabetes remission and complication reporting differ between studies
- Some surgeons have reported cases of severe malnutrition requiring revision, highlighting the importance of careful technique and follow-up
What this means for patients
SASI appears to be an effective metabolic operation in the short and medium term, especially for patients with type 2 diabetes. However, patients should understand that its long-term safety and durability are not yet known with the same confidence as sleeve gastrectomy or Roux-en-Y gastric bypass. Choosing SASI should be a shared decision between patient and surgeon, made after weighing the potential benefits against the uncertainties.
Expected weight loss
| Time after surgery | Typical reported range | Notes |
|---|---|---|
| 6 months | Rapid loss, often more than half of excess weight | Similar early trajectory to sleeve and bypass |
| 12 months | Roughly 70 to 90 percent of excess weight in reported series | Results vary widely between patients |
| 2 to 3 years | Generally maintained in available studies | Fewer patients followed, so less certainty |
| 5 years and beyond | Limited data | Long-term outcomes still being studied |
SASI and Type 2 Diabetes
SASI was originally developed with type 2 diabetes in mind, and its metabolic effects are the main reason surgeons choose it.
Why SASI may help diabetes
- Rapid delivery of nutrients to the ileum increases GLP-1, which stimulates insulin release and reduces glucagon
- Removal of most of the stomach reduces ghrelin and appetite
- Weight loss improves insulin sensitivity in the liver and muscles
- Changes in bile acids and the gut microbiome may contribute to improved glucose control
Who is most likely to benefit
As with other metabolic operations, the chance of diabetes remission is highest in patients with a shorter duration of diabetes, no or low-dose insulin use, fewer medicines and good residual insulin production. Patients with long-standing, insulin-dependent diabetes may still achieve significant improvement and reduced medicine needs, even if complete remission is less likely.
Managing medicines after surgery
Blood sugar may fall quickly after SASI. Insulin and sulfonylureas usually need to be reduced or stopped immediately after surgery to prevent hypoglycaemia. Metformin and other medicines are adjusted according to glucose readings. Patients receive a written medicine plan and close follow-up in the first weeks.
Long-term monitoring
Even when diabetes goes into remission, annual HbA1c tests, kidney function checks and eye examinations for those with previous retinopathy should continue, because diabetes can return over time, particularly with weight regain.
Evaluation Before SASI Surgery
A thorough evaluation is essential before any metabolic operation, and particularly before one that alters the intestine.
| Assessment | Purpose |
|---|---|
| Medical history and examination | Weight history, diabetes duration and treatment, previous operations, bowel habits and medicines |
| Blood tests | Blood count, iron studies, vitamin B12, folate, vitamin D, calcium, albumin, kidney and liver function, HbA1c, C-peptide, lipids, thyroid function and coagulation |
| Upper endoscopy | Essential to detect reflux oesophagitis, hiatal hernia, Barrett's oesophagus, ulcers and Helicobacter pylori, as these influence whether a sleeve-based operation is appropriate |
| Abdominal ultrasound | Gallstones and fatty liver |
| Heart and lung assessment | ECG, echocardiography when indicated and sleep apnoea screening |
| Nutrition assessment | Eating habits, protein intake, baseline deficiencies and readiness for lifelong supplementation |
| Psychological assessment | Screening for depression, eating disorders and alcohol use |
| Anaesthetic review | Airway, medicines and overall surgical risk |
Reflux assessment is critical
Because SASI includes a sleeve gastrectomy, any existing reflux disease must be carefully assessed. Patients with significant reflux symptoms, erosive oesophagitis or Barrett's oesophagus are generally better served by Roux-en-Y gastric bypass. When the diagnosis is uncertain, pH monitoring may be performed.
Baseline bowel function
Patients with frequent loose stools, irritable bowel syndrome with diarrhoea, lactose intolerance or previous bowel surgery should discuss these with the surgeon, as SASI can change bowel habits.
Preparing for SASI Surgery
Liver-shrinking diet
Most patients follow a low-calorie, high-protein diet for about two weeks before surgery. This reduces the size of the fatty liver and makes laparoscopic surgery safer and easier.
Stop smoking
Smoking increases the risk of leaks, ulcers at the connection, blood clots and chest infections. All forms of nicotine, including cigarettes, shisha and vaping, should be stopped at least six weeks before surgery and avoided permanently.
Medicines
- Avoid anti-inflammatory painkillers (NSAIDs) before and after surgery because of the ulcer risk
- Plan adjustments for blood thinners and diabetes medicines
- Inform the team about GLP-1 receptor agonists such as semaglutide or tirzepatide, which may need to be paused before anaesthesia
- Review extended-release and enteric-coated medicines, which may be absorbed differently after surgery
Correct existing deficiencies
Iron, vitamin D and vitamin B12 deficiencies are common in people with obesity. Correcting them before surgery helps recovery and reduces the risk of more severe deficiencies later.
Practical preparation
- Buy protein supplements, a bariatric multivitamin and measuring tools
- Practise eating slowly and separating fluids from meals
- Increase daily walking
- Arrange time off work, usually two to three weeks for desk work
- Plan support at home for the first week or two
Pregnancy planning
Women are advised to avoid pregnancy for 12 to 18 months after surgery and should discuss reliable contraception before the operation.
The SASI Procedure Step by Step
SASI is performed under general anaesthesia using laparoscopic or robotic techniques through several small incisions. The operation usually takes about two to three hours.
- Access and inspection: the abdomen is inflated with carbon dioxide and the camera and instruments are introduced.
- Hiatal assessment: the area where the oesophagus enters the abdomen is examined and any hiatal hernia is repaired.
- Sleeve gastrectomy: the blood vessels along the outer curve of the stomach are divided, and a stapler is used along a calibration tube (bougie) to create a narrow sleeve, removing about 75 to 80 percent of the stomach.
- Measuring the small intestine: the surgeon measures backwards from the ileocaecal valve to identify the point for the connection, commonly about 250 to 300 cm. Many surgeons also measure the total length of the small intestine to tailor the design.
- Creating the gastro-ileal anastomosis: the selected loop of ileum is brought up and connected side-to-side to the lower part of the stomach (antrum), creating an opening commonly about 3 cm wide.
- Additional steps: some surgeons add a small stitch or anti-reflux measures to the loop to reduce bile reflux, depending on their technique.
- Leak test: the staple line and connection are checked for leaks.
- Closure: the removed part of the stomach is extracted through one incision, and the small incisions are closed.
Technical variations
SASI technique is not yet fully standardised. Variations include the size of the bougie, the distance between the pylorus and the connection, the width of the anastomosis and the length of the bypassed intestine. Some surgeons use a jejunal rather than ileal connection (SASJ) to reduce malabsorption. Ask your surgeon which technique they use and why.
Enhanced recovery
Perioperative care follows Enhanced Recovery After Surgery (ERAS) principles, including multimodal pain control, prevention of nausea, early walking and early oral fluids.
Hospital Stay and Early Recovery
Most patients walk within hours of surgery and stay in hospital for about one to three nights, depending on recovery.
| Time | What to expect |
|---|---|
| Day of surgery | Walking with help, breathing exercises, sips of water when allowed, pain control and blood clot prevention |
| Days 1 to 2 | Gradual increase in fluids, more walking, blood tests and monitoring |
| Discharge | When fluids are tolerated, pain is controlled and the patient walks independently |
| Week 1 | Liquid diet, regular short walks, blood thinner injections when prescribed |
| Weeks 2 to 3 | Puréed foods; return to desk work for many patients |
| Weeks 4 to 6 | Soft foods, more daily activity and gradual exercise |
Medicines after discharge
Patients typically go home with pain relief that avoids NSAIDs, an acid-reducing medicine for several months to protect the sleeve and the connection, blood clot prevention when indicated, a bariatric multivitamin and, in some cases, ursodeoxycholic acid for about six months to reduce the risk of gallstones during rapid weight loss.
Changes in bowel habits
Some patients notice softer or more frequent stools after SASI, particularly after fatty meals. This usually settles as the diet progresses. Persistent diarrhoea, oily stools or significant weight loss beyond expectations should be reported, as they may indicate malabsorption.
Diet Stages After SASI
The diet after SASI follows the same staged approach as other bariatric operations, with particular attention to protein intake and fat content.
| Stage | Timing | Foods | Key goals |
|---|---|---|---|
| Liquids | About weeks 1 to 2 | Water, clear broths, sugar-free drinks, protein shakes, low-fat milk or lactose-free alternatives | 1.5 to 2 litres of fluid daily; begin protein intake |
| Puréed foods | About weeks 2 to 4 | Blended lean protein, eggs, yoghurt, cottage cheese and puréed vegetables | Small portions, protein first |
| Soft foods | About weeks 4 to 6 | Tender fish, minced meat, soft chicken, cooked vegetables and soft fruit | Chew thoroughly and stop at the first sign of fullness |
| Regular healthy diet | From about week 6 to 8 | Balanced meals built around protein, vegetables, fruit and whole grains | Lifelong habits, about three small meals plus protein snacks |
Protein is the priority
Protein malnutrition is one of the most important potential complications after operations that bypass part of the small intestine. Patients should aim for at least 60 to 80 grams of protein daily, or more if advised, and should prioritise protein at every meal. Low albumin, swelling of the legs, severe hair loss or excessive weakness may indicate protein deficiency and require prompt review.
Fat and sugar
Very fatty meals may cause loose or oily stools and cramping, and sugary foods may cause dumping symptoms in some patients. A diet rich in lean protein, vegetables and complex carbohydrates is best tolerated.
General rules
- Eat slowly over 20 to 30 minutes and chew thoroughly
- Separate drinks from meals by about 30 minutes
- Sip water throughout the day to avoid dehydration
- Avoid carbonated drinks in the early months
- Avoid alcohol, particularly in the first year
- Do not skip supplements
Vitamins and Lifelong Nutrition Monitoring
Lifelong supplementation and monitoring are essential after SASI. Because the operation includes an intestinal bypass, and because the proportion of food passing through each route varies, deficiencies can develop even years after surgery. Recommendations are based on the AACE/TOS/ASMBS nutrition guidelines for bariatric procedures and are adjusted according to each patient's blood tests.
| Supplement | Typical recommendation | Why it matters |
|---|---|---|
| Bariatric multivitamin with minerals | Daily, lifelong | Covers thiamine, folate, zinc, copper and other micronutrients |
| Vitamin B12 | Oral daily dose or periodic injections according to blood levels | The sleeve reduces intrinsic factor and acid; deficiency causes anaemia and nerve damage |
| Iron | As needed according to blood tests, especially in menstruating women | Iron deficiency anaemia remains possible |
| Calcium citrate | About 1200 to 1500 mg daily in divided doses | Protects bone health |
| Vitamin D3 | At least 3000 IU daily, adjusted to blood levels | Supports calcium absorption and bone health |
| Fat-soluble vitamins A, E and K | Monitored and supplemented as needed | Absorption may be reduced when part of the intestine is bypassed |
| Protein | At least 60 to 80 g daily | Prevents muscle loss and protein malnutrition |
Monitoring schedule
| Time | Typical tests |
|---|---|
| 3 months | Blood count, kidney and liver function, albumin and glucose |
| 6 months | Blood count, iron studies, vitamin B12, folate, vitamin D, calcium, parathyroid hormone and albumin |
| 12 months | Full nutritional panel including vitamins A and E, zinc and copper, plus HbA1c and lipids |
| Every year afterwards | Full nutritional panel, albumin and bone health markers |
| Every two years or as advised | Bone density scan in selected patients |
International patients can have these tests performed in their home country and share the results with the team for review.
Risks and Complications of SASI
SASI carries the risks of a sleeve gastrectomy plus those related to the intestinal connection. Published complication rates vary between centres, and long-term data are still limited.
Early complications
| Complication | Details |
|---|---|
| Leak | From the sleeve staple line or the connection; uncommon but serious; causes fever, fast heart rate and abdominal pain |
| Bleeding | From staple lines or inside the bowel; most cases settle with observation or transfusion |
| Blood clots | Reduced by early walking, compression and blood thinners |
| Dehydration and nausea | Common in the first weeks if fluid intake is low |
| Wound infection | Usually minor |
Later complications
| Complication | Details and prevention |
|---|---|
| Reflux | The sleeve component can cause or worsen acid reflux; bile reflux into the stomach from the connection has also been reported |
| Marginal ulcer | Ulcer at the connection; smoking and NSAIDs are major risk factors |
| Protein malnutrition | Reported in a minority of patients, particularly when most food passes through the shortcut; may require nutritional support or revision |
| Micronutrient deficiencies | Vitamin B12, vitamin D, iron, calcium and fat-soluble vitamins; prevented by supplements and monitoring |
| Diarrhoea and bowel changes | Usually improve over time with dietary adjustment |
| Dumping symptoms | Possible because food can reach the intestine quickly; managed by avoiding sugar |
| Gallstones | More likely during rapid weight loss; preventive medicine may be advised |
| Weight regain | Possible over time; long-term data are limited |
| Internal hernia or bowel obstruction | Less common than after Roux-en-Y bypass, but possible |
Revision and reversibility
One potential advantage of SASI is that the connection can be taken down in a further operation, converting the anatomy back to a sleeve gastrectomy, if severe malnutrition or another serious complication occurs. Other revisions are also possible depending on the problem. Like any revisional operation, these procedures carry their own risks.
Warning signs that need urgent attention
- Fever, fast heart rate, worsening abdominal pain or breathlessness in the first weeks
- Persistent vomiting or inability to keep fluids down
- Black or bloody stools, or vomiting blood
- Severe or persistent diarrhoea, swelling of the legs or extreme weakness
- Severe abdominal pain at any time after surgery
- Painful swelling of one leg or chest pain
Long-Term Life After SASI
Exercise
Walking begins on the day of surgery. Structured exercise usually starts after about four to six weeks, and strength training after about six to eight weeks. Regular physical activity preserves muscle mass, supports weight maintenance and improves metabolic health.
Medicines
- Avoid NSAIDs long term because of the ulcer risk
- Review extended-release medicines and medicines with narrow therapeutic ranges, as absorption may change
- Always tell new doctors and pharmacists that you have had SASI surgery
Pregnancy
Women should wait 12 to 18 months after surgery before conceiving, plan pregnancy with their doctors, and continue supplements with close monitoring of iron, folate, vitamin B12, vitamin D and protein status during pregnancy.
Endoscopy
Because the duodenum remains in continuity, standard upper endoscopy can reach the duodenum and ERCP can be performed if bile duct problems arise. This is a practical advantage over Roux-en-Y and one-anastomosis gastric bypass.
Body contouring
Excess skin after major weight loss can be addressed with body contouring surgery once weight has been stable for six to twelve months, usually 18 months or more after surgery.
Ongoing support
Regular follow-up with the surgical team, dietitian and, when needed, psychological support helps patients maintain their results and detect problems early.
SASI as a Revision After Sleeve Gastrectomy
Some centres use SASI as a revisional option for patients with insufficient weight loss or weight regain after sleeve gastrectomy, because the sleeve is already in place and only the connection needs to be added. This approach is sometimes called conversion to SASI.
When it may be considered
- Weight regain or insufficient weight loss after sleeve gastrectomy without significant reflux
- Persistent or recurrent type 2 diabetes after sleeve
- Patients who wish to keep endoscopic access to the duodenum
When other options are preferred
If reflux is the main problem after a sleeve, conversion to Roux-en-Y gastric bypass is usually the preferred option, because SASI keeps the sleeve and may not resolve reflux. If the sleeve has dilated significantly, a re-sleeve may be combined with other procedures. Each case requires endoscopy, imaging and a full review. Our guide to revision bariatric surgery explains the options in more detail.
Evidence
Data on SASI as a revisional procedure are limited to small series. Revisional surgery generally carries higher risks than primary surgery, and patients should understand these before deciding.
SASI Surgery in Jordan for International Patients
Patients from the Gulf, the United Kingdom, Europe and North America travel to Amman for metabolic surgery because of experienced bariatric surgeons, modern hospitals and short waiting times. Because SASI requires careful selection and long-term nutritional follow-up, planning is especially important.
A typical plan
- Send your height, weight, diabetes history, medicine list, recent blood tests and any endoscopy reports for a remote review.
- Receive an initial opinion on whether SASI or another operation is more suitable, with a list of required tests.
- Arrive in Amman for consultation, blood tests, endoscopy and anaesthetic assessment.
- Have surgery, followed by about one to three nights in hospital.
- Stay in Jordan for about 7 to 10 days for early follow-up and a fit-to-fly assessment.
- Continue remote follow-up with regular laboratory tests at home.
Long-term follow-up at home
Before travelling, identify a local doctor who can arrange blood tests and see you if problems arise. You will receive a written summary of your operation, medicines and supplement plan. Because nutritional deficiencies after SASI may develop slowly, regular laboratory monitoring is essential even when you feel well.
Flying after surgery
Walk regularly during the flight, stay well hydrated, wear compression stockings and use blood thinner injections if prescribed.
Our international patient team assists with appointments, transfers, accommodation and communication throughout your stay.
Choosing a Surgeon for SASI
Because SASI is a newer and less standardised operation, the experience and judgement of the surgeon are particularly important. Look for:
- Specialist training in bariatric and metabolic surgery and experience with sleeve gastrectomy, gastric bypass and revisional surgery
- A clear explanation of why SASI is being recommended over established alternatives
- Transparency about the technique used, including limb measurements
- Honest discussion of the limitations of current evidence
- A structured programme of lifelong nutritional follow-up
- An accredited hospital with intensive care, endoscopy and interventional radiology
About Dr. Mohammad Al-Zaitawi
Dr. Mohammad Al-Zaitawi is a consultant surgeon in Amman with the Jordanian Board in General Surgery and a subspecialty in bariatric surgery. He is a Fellow of the American College of Surgeons and a Fellow of the International College of Surgeons, and holds a diploma in laparoscopic and bariatric surgery from Strasbourg, France. He performs sleeve gastrectomy, gastric bypass, SASI and revisional bariatric surgery, and recommends the operation after a full assessment of each patient. You can review his profile and credentials and read patient reviews.
Questions to ask at your consultation
- Why are you recommending SASI rather than a sleeve, Roux-en-Y bypass or mini bypass for me?
- What does the current evidence show, and what is still uncertain?
- What limb lengths and connection size do you use?
- How will my reflux be assessed and managed?
- Which supplements will I need, and how often will my blood tests be checked?
- What happens if I develop malnutrition or other complications?
- How long should I stay in Jordan before flying home?
Frequently Asked Questions
What does SASI stand for?
How is SASI different from gastric bypass?
How much weight can I lose with SASI?
Is SASI good for type 2 diabetes?
Is SASI an established operation?
Does SASI cause reflux?
Will I need vitamins after SASI?
Can SASI cause malnutrition?
Is SASI reversible?
How long does SASI surgery take?
How long is the hospital stay?
When can I return to work after SASI?
Can SASI be done after a previous sleeve?
How long should international patients stay in Jordan?
How much does SASI cost in Jordan?
Conclusion
SASI combines a sleeve gastrectomy with a single connection to the lower small intestine, creating two pathways for food. Early studies show strong weight loss and impressive improvement in type 2 diabetes, while keeping the duodenum accessible for endoscopy. However, SASI is newer than sleeve gastrectomy and gastric bypass, its long-term outcomes are still being established, and it requires careful patient selection and lifelong nutritional monitoring.
At Dr. Mohammad Al-Zaitawi's center in Shmeisani, Amman, SASI is offered as one of several options after a detailed assessment of your BMI, diabetes, reflux and lifestyle, with an honest discussion of benefits, risks and uncertainties, and a structured follow-up plan whether you live in Jordan or abroad.
Your next steps
- Gather your recent blood tests, HbA1c, endoscopy reports and medicine list.
- Request a free consultation for a remote review.
- Discuss whether SASI or an established alternative suits you best.
- Read our guides on gastric bypass, mini gastric bypass and sleeve gastrectomy.
This guide is for general information and does not replace individual medical advice. Treatment decisions are made only after a personal assessment by your surgeon.
Medical note from Dr. Mohammad Al-Zaitawi
SASI can be a strong option for selected patients, especially with type 2 diabetes, but it is newer than sleeve and bypass. I recommend it only after a full assessment and an honest discussion of the alternatives and the need for lifelong follow-up.
What international patients say
Selected patient feedback connected to this procedure.
International Patient
The coordination before travel and the follow-up after surgery were clear and professional.
Related articles and success stories
Helpful links for patients comparing treatment options and planning their journey.
Scientific references and guidance
These sources support the medical information on this page. If you want this guidance applied to your own case, send us your details for an initial review.
Reviewed by Dr. Mohammad Al-Zaitawi
Prefer a quicker route? Try the free case review or see bariatric surgery costs in Jordan.